



 Inglés (pdf)
 Articulo en XML
 Referencias del artículo

 Traducción automática
 Enviar articulo por email
 Citado por SciELO
 Similares en
SciELO

 Permalink


Introduction
Dental caries (DC) arise due to an imbalance in the demineralization and remineralization processes in dental tissues, leading to the destruction of dental tissue (1). This imbalance is related to changes in the population of cariogenic bacteria which cause alterations in salivary pH (2). According to the World Health Organization, about 2 billion people with permanent teeth and 600 million with primary teeth suffer from this disease worldwide (3).
Conventional methods of DC removal, such as rotary systems (RS), have disadvantages such as the generation of pressure and heat that can damage the dental pulp, noise, vibration, pain, and the need for anesthesia (4). Therefore, less invasive methods have been analyzed (5,6). The first generation of chemical-mechanical agents (CMA) used sodium hypochlorite (NaClO) and, subsequently, papain-based products, such as Papacarie Duo Gel, Carie Care, and Brix 3000, became available (7).
CMA are considered viable alternatives because they allow the selective removal of infected dentin without damaging healthy dentin (8). In addition, they are useful for clinical care in uncooperative patients, pediatric patients, and/ or patients with different discapacities (9,10). In 1998, the Carisolv system (11) containing a gel with 0.5% NaClO and three amino acids (12,13,14) that dissolve carious dentin was introduced to the market (15). Among other CMA options, Papacarie uses papain as a component to partially degrade collagen fibers (16), preserving healthy dentin (17-18).
Dentists in clinical practice need to know the benefits of the materials marketed based on scientific evidence to help make the most adequate treatment decisions. Prevention of caries recurrence, complete elimination of bacteria, and preservation of dentin are essential in clinical practice. Therefore, the present systematic review aimed to compare the efficacy and efficiency of CMA versus RS for the removal of DC from permanent teeth based on evidence from in vitro studies.
Materials and methods
Protocol and registry
The protocol of this systematic review was registered in INPLASY (INPLASY202320001). The review was carried out following the guide- lines of the Preferred Reporting Items for Systematic Reviews and Meta-analyses (PRISMA) as a tool for verification and quality control of the review process.
Search strategy
An article search was conducted up to July 31, 2022, in five electronic databases (PubMed, Ebsco, Scopus, ScienceDirect, LILACS) and gray literature. The search used MeSH terms or keywords combined with Boolean operators (AND and OR) such as: «dental caries», «chemical agent», «Papacarie», «Carisolv», «Brix 3000», «rotary system» and
«permanent tooth». In addition, a manual search was performed in two academic search engines and five specialized journals: Dental Research Journal, Journal of The American Dental Association, Journal of Dentistry, Operative Dentistry, and The International Journal of Periodontics & Restorative Dentistry (Table 1).
Selection of studies
Study selection was based on the PICOS questions, the components of which were: (P) permanent human teeth with DC with cavities in dentin obtained from extractions; (I) CMA complemented with manual mechanical removal; (C) high or low-speed RS, (O) removal of DC according to efficacy (primary outcome) evaluated with a parameter such as histological, microbiological, radiographic analysis or physicochemical-mechanical properties and/or according to the efficiency (secondary outcome) of the technique based on the shortest time for removal; and (S) in vitro experimental studies.
Eligibility criteria
The criteria for studies to be included in this review were: a) to include samples of permanent human teeth detected as dentin caries lesions; b) comparison of at least one CMA (non-conventional method) with RS (conventional method or control group) for DC removal; c) CMAs such as Carisolv, Papacarie, Brix 3000, and Carie Care complemented only with manual mechanical removal using special instruments or curette; d) initial or final verification of DC removal analyzed without restriction of the visual, tactile, chemical or fluorescence detection method used; e) histological analysis (gold standard) by optical (OM), stereoscopic (SM), confocal (CM), or scanning electron microscopy (SEM) to verify quantitative (presence, quantity, or extent) or qualitative DC removal with the presence of dentin tubules (DT) or smear layer (SL); microbiological analysis of the presence of bacterial deposit; radiography with conventional radiographs or tomography, physical-mechanical properties of the surfaces such as hardness, microhard- ness (MH), or bond strength with a universal testing machine (UTM), evaluation of chemical changes of the mineral content with an energy dispersive X-ray system (EDX); f) time measurement of DC removal evaluated with stopwatch; g) in vitro experimenttal design; h) full-text articles, and i) in Spanish, Portuguese, or English language. The exclusion criteria were: a) CMAs complemented with high or low-speed mechanical removal; b) randomized and non-randomized clinical trials; c) case reports or case series; d) preclinical studies; e) animal studies; f) in vivo designs; g) letters to the editor; h) literature or systematic reviews; i) books or book chapters and theses; and j) duplicates.
Data extraction
The extraction of the study articles, previously calibrated for selection (Cohen's Kappa test: K=0.84), was carried out in phases by independent review by two researchers (J.Q.R. and S.M.C.). First, a primary search was made to select articles based on the database of their origin, the Zotero manager was used, then duplicate articles, as well as titles and abstracts, were eliminated. Finally, articles that did not meet the eligibility criteria were excluded. After that, the articles were analyzed in full text for exhaustive review of the qualitative synthesis. The participation of a 3rd, 4th and 5th author was required to decide on the inclusion of certain studies (C.M.S., K.C.S. and J.D.V.)
Outcome measures
The outcomes of interest were: author (country, year), sample, initial DC verification, CMA group, CMA application, RS group, final DC verification, primary measurement, primary result, secondary measurement, and secondary result. The variable of time was expressed as minutes (min). Qualitative results were presented or quantified as percentages, and quantitative results were expressed as means and standard deviation or median. The final review of the extracted data was analyzed by three additional authors (C.M.S., K.C.S., and J.D.V.).
Risk of bias in studies
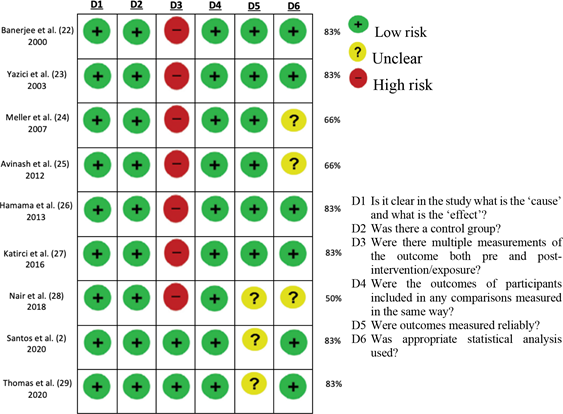
The methodological quality of the articles was independently assessed by three reviewers (J.Q.R., S.M.C., and J.D.V.) using the Joanna Briggs Institute (JBI) critical appraisal checklist for quasi-experimental studies (19) adapted to the evaluation of in vitro studies according to six items: D1. Was the 'cause' and 'effect' clear? D2. Was there a control group? D3. Were multiple outcome measurements taken before and after the experiment? D4. Were the results measured in the same way for the sample included in the comparisons? D5. Were the results reliably measured? and D6. Was appropriate statistical analysis used? (Table S1). The risk level was: low (>70%), moderate (50%-69%), and high (≤49%) according to risk of bias (20). The final score for each article was obtained by calculating the percentage of positive (yes) responses selected (21). A meta-analysis was not considered due to the heterogeneity of the studies included.
Results
Study selection
A total of 914 publications were identified in the electronic databases, 905 of which were extracted from databases and 9 from other sources. The data was filtered by eliminating duplicates (n=49) and screened based on titles and abstracts (n=845) to obtain 20 eligible articles. After full- text reading, 10 studies were excluded because they did not meet the necessary outcomes, and 1 due to contradictory results (Table S2). Finally, 9 articles were selected for the qualitative synthesis of the present systematic review. This process is illustrated in the PRISMA flow diagram (Figure 1).
Characteristics of the studies included
The in vitro studies included evaluated a total of 337 human permanent molars with the presence of cavitated caries lesion in dentin. Five of the nine articles applied two or more DC diagnostic criteria (2, 23, 26, 27,29). The methods of initial verification of the lesion were distributed into visual (2, 22, 24,25,26, 28, 29), radiographic or tomographic (2, 27, 29), tactile (26), and laser fluorescence (23). The number of specimens per group ranged from 8 to 40 in CMA and RS with the split-tooth technique in all studies except 1 article (24). The final verification criteria for DC removal were visual and tactile without (2, 22,23,24,25, 28) or with detection dye (27, 29), and detection dye alone (26) (Table 2).
Evaluation groups
The CMA most frequently studied was Carisolv in 8 publications (22,23,24,25,26,27,28,29), while 3 articles evaluated Papacarie (2, 26, 28), 2 Carie Care (28, 29) and 1 study evaluated the use of Brix 3000 (2). Carisolv was used at a concentration of 0.25% (25,26,27,28,29) and 0.5% (22,23,24) and was mostly applied at 30s (22, 23, 25,26,27,28,29). Papacarie was applied for 30s (26, 28) and 40s (2), while Carie Care was applied for 30s (28, 29) and Brix 3000 for 120s (2). All the CMAs were applied with similar protocols of application within a controlled time, mechanical- manual removal with an instrument, reapplication, re-removal until no turbidity was observed, and cleaning with water. RS were more frequently used at low speed in 8 articles (2, 22-27, 29) in contrast to 1 article that applied high speed (28), with the use of round bur in all the articles (Table 2).
Measurement type
The primary measurement technique most commonly used to evaluate DC treatment was histological analysis in 4 studies (22, 24, 26, 27) assisted with CM (22), SM (24, 27), and 2000× SEM (26) equipment. Fewer studies evaluated the effect on the chemical composition of dentin with EDX of calcium (Ca), phosphorus (P) (26, 27) and Ca/P (26,27,28); the physical mechanical characteristic of MH with Knoop indenter at 25 g/5s (2) and 50g/15s (27) and Vickers at 50g/15s (26); microbiological analysis of bacterial deposits in histological sections with OM (23) and 5000× SEM (25); radiographic evaluation with cone beam computed tomography (CBCT) (29) and bond strength with the microtraction technique using UTM (28). Secondary measurement of DC removal time was analyzed in most of the studies (2, 22,23,24,25,26, 29).(Table 2).
Histological observations
Three of the nine studies reported quantitative evaluation of Carisolv that was statistically higher compared to low-speed RS (p<0.05) in relation to the amount of residual caries (RC) (∆25µm) (24), the presence of RC (∆15%) (27) and the extracted caries volume (ECV) (p<0.001) using autofluorescence by CM (∆5.4 to 9.5%) (22). The study with qualitative results observed with SEM of SL-coated DTs showed an absence with Papaca- rie, partial/total presence with Carisolv and total presence with low-speed RS (26) (Table 2).
Microbiological analysis
One study (23) reported a lower presence of microbial deposits with low-speed RS than with Carisolv (∆57.3%), especially at the level of the dentin-enamel junction (DEJ) (∆42.9%) compared to the cavity floor (∆14.4%), with statistically significant differences (p<0.01). Furthermore, another study found differences between the two removal techniques (p<0.05) (25) (Table 2).
Chemical evaluation
Three of the nine studies that analyzed the chemical components of dentin with EDX found no statistically significant differences between low- (26, 27) or high-speed RS (28) versus Carisolv (26,27,28), Papacarie (26, 28) and Carie Care (28) in relation to Ca (26, 27), P (26, 27) and the Ca/P ratio (26, 27, 28) (p≥0.05) (Table 2).
Radiographic examination
The study (29) that evaluated changes in ECV using CBCT found a statistically significant greater change with RS (≈110%) compared to Carisolv and Carie Care (≈25 to 30%) (p<0.05). The efficacy of Carisolv and Carie Care was similar (p≥0.05) (Table 2).
Physical-mechanical properties
The MH of residual dentin (RD) in two studies determined that low-speed RS was statistically superior (p<0.05) compared to Carisolv (26, 27) or Papacarie analyzed with Vickers ∆70 (26) and Knoop ∆7 (27), with no differences between Carisolv and Papacarie (p≥0.05) (26) (26, 27). However, other studies reported that RS was similar to Papacarie and Brix 3000 regarding MH (2) and Carisolv, Papacarie, and Carie Care in relation to bond strength (28) (p≥0.05) (Table 2).
Caries removal time
The mean time for DC removal ranged from 0.9 to 4.8min with low-speed RS (2, 22,23,24,25,26, 29), 1.42min with Brix 3000 (2), from 1.84 to 5.19min with Papacarie (2,26), 3.08min with Carie Care (29) and from 3.61 to 8.9min with Carisolv (29). The time was statistically lower with RS compared to Carisolv (22-26), Papacarie (2), Brix 3000 (2), and Carie Care (29). The removal time of DC was also shorter with Papacarie vs. Carisolv (26) and Brix 3000 vs. RS (2) (p<0.05) but was similar between Papacarie and RS (26) and Carisolv and Carie Care (29) (p≥0.05) (Table 2).
Certainty of the evidence and risk of bias
Only one study evaluated the certainty of the evidence indicating the statistical parameter of power in the variable of removal time, which was a reliable 85.5% (2). However, other authors did not perform this evaluation (22-28, 29). Evaluation of the methodological quality according to the modified JBI critical evaluation for quasi-experimental studies determined that all the studies were clear about the direction of cause (agent or treatment system) and effect (DC removal), presented a control group (RS) and analyzed group comparisons in the same way. Most studies had reliable results with histological or microbiological methods (22-27) and used adequate statistical analyses (2, 22, 23, 26, 27, 29), but did not present measurements before the experiment (22-28) (Table S3). The level of risk of bias was low in six studies (2, 22, 23, 26, 27, 29) and moderate in three studies (24, 25, 28) (Figure 2).
Table 1 Search strategy for descriptors across different databases.
| MedLine/PubMed |
| n=561 |
| ((((((((((((((((((((((((caries) OR (tooth decay)) OR (tooth decay in adult teeth)) OR (tooth decay in permanent teeth)) OR (dental caries)) OR (dental caries in adult teeth)) OR (dental caries in permanent teeth)) OR (permanent teeth)) OR (permanent tooth)) OR (adult tooth)) OR (adult teeth)) OR (cavities)) OR (tooth cavity)) OR (cavity)) OR (decay)) OR (mature teeth)) OR (tooth demineralization in adult teeth)) OR (tooth demineralization in permanent teeth)) OR (carious lesions in permanent teeth)) OR (carious lesions in adult teeth)) OR (dental decay in adult teeth)) OR (dental decay in permanent teeth)) AND (((((((((((((((((((chemomechanical) OR (atraumatic restorative treatment)) OR (ART)) OR (MID)) OR (minimal invasive dentistry)) OR (papacarie)) OR (papain)) OR (brix 3000)) OR (carie care)) OR (GK-101E)) OR (carisolv)) OR (caridex)) OR (CMCR)) OR (carica papaya)) OR (chemomechanical caries removal)) OR (micro invasive treatment)) OR (non rotary)) OR (enzymes)) OR (in vitro))) AND ((((((((((((((((((conventional method) OR (burs)) OR (bur)) OR (rotary)) OR (mechanical)) OR (drilling)) OR (rotary drill)) OR (rotary instruments)) OR (dental handpiece)) OR (dental burs)) OR (dental bur)) OR (drill)) OR (conventional drill)) OR (traditional drill)) OR (conventional drilling)) OR (traditional drilling)) OR (conventional rotary method)) OR (traditional treatment of removing decay))) AND ((((((((((efficiency of caries removal) OR (effectiveness of caries removal)) OR (efficacy of caries removal)) OR (assessment of caries removal)) OR (evaluation of caries removal)) OR (remaining decay)) OR (absence of soft caries)) OR (removal of decay)) OR (removal of caries)) OR (removal of infected caries)) |
| EBSCO |
| n=96 |
| chemomechanical agent caries OR conventional rotary excavation AND in vitro study AND efficiency AND effectiveness AND efficacy AND dental caries AND permanent teeth AND low-speed rotary instruments AND secondary dentition NOT systematic review or meta-analysis |
| Scopus |
| n=10 |
| ( chemomechanical AND caries AND removal OR dental AND high AND speed AND technique AND dental AND caries AND permanent AND teeth AND permanent AND tooth AND in AND vitro AND efficacy AND effectiveness ) AND NOT ( primary AND NOT teeth ) AND NOT ( systematic AND NOT review ) AND NOT ( primary AND NOT molars ) |
| ScienceDirect |
| n=233 |
| Chemomechanical caries removal OR Dental High-Speed Technique AND in vitro AND efficiency AND effectiveness AND efficacy AND dental caries AND permanent teeth AND carbide bur |
| LILACS |
| n=5 |
| chemomechanical (Palavras do título) or Dental High-Speed Equipment (Palavras do título) and vitro (Palavras do título) |

Table 2 Characteristics of the studies included.
| Author (Country, year) | Sample | Initial DC verification | CMA Group | CMA Application | RS Group | Final DC verification | Primary measurement | Primary result | Secondary measurement | Secondary result |
|---|---|---|---|---|---|---|---|---|---|---|
| Banerjee et al. (England, 2000) (22) | 40 permanent molars with carious lesions with cavities in dentin | Visual criteria | Carisolv/Gel NaClO (0.5%) pH: 11 (n=20, split tooth) | Applied for 30 seconds, manual removal with Carisolv instrument, reapplication, and removal until no turbidity is observed, cleaning of the cavity with a moistened cotton ball, and final rinse. | Conventional low speed: tungsten carbide burr #3. (n=20, split tooth) | Visual and tactile criteria (dental probe). | Histological analysis: ECV observed with fluorescence by CM (15 µm). | The change in ECV was statistically higher with RS (13.73 to 17.8 ± 1.28 to 2.02%) than with CMA (8.30 to 10.13 ± 1.48 to 1.63%) (p<0.001). | Time: from the beginning of the application or rotation until the end of the removal, counted with a stopwatch. | The DC removal time was statistically higher with CMA (3.61 ± 1.54 min) than with RS (0.95 ± 0.29 min) (p<0.001). |
| Yazici et al. (Türkiye, 2003) (23) | 14 permanent molars with carious lesions with cavities in dentin | DIAGNOdent laser fluorescence values between 40 and 50. | Carisolv/Gel NaClO (0.5%) pH: 11 (n=14, split tooth) | Applied for 30 seconds, manual mechanical removal with the Carisolv instrument, reapplication and removal until no clouding is observed, cleaning the cavity with a moistened cotton ball, and final rinsing | Conventional low speed: #3 steel round milling cutter. (n=14, split tooth) | Visual and tactile criteria. | Microbiological analysis: Bacterial deposits were observed in histological sections with toluidine blue by OM (40 and 100×; 5 µm). | The presence of bacterial deposits was statistically higher with CMA (total 64.3%: 42.9% in the DEJ and 21.4% in the cavity floor) than with RS (total 7%: 0% DEJ and 7% in the cavity floor) (p<0,01). | Time: from the beginning of the application or rotation until the end of the removal, counted with a stopwatch. | DC removal time was statistically higher with CMA (4.53 ± 0.89 min) than with RS (1.93 ± 8.23 min) (p<0.01). |
| Meller et al. (Germany, 2007) (24) | 24 permanent molars with carious lesions with cavities in dentin | Visual criteria | Carisolv/gel NaClO (0.5%) pH: 11 (n=12) | They were applied for 20 s, manual mechanical removal with the recommended instrument, cleaning the cavity with air and water spray. | Conventional low speed: tungsten carbide round burr #8-16. (n=12) | Visual and tactile criteria (dental explorer). | Histological analysis: RC observed with liquid caries detector using SM (7×; 400 µm). | The amount of RC was statistically higher with CMA (57 ± 39 µm) than with RS (32 ± 20 µm) (p<0.05). | Time: from the beginning of the application or rotation until the end of the removal, counting with a stopwatch. | DC removal time was statistically higher with CMA (8.9 min) than with RS (4.8 min) (p<0.05). |
| Avinash et al. (India, 2012) (25) | 15 permanent molars with carious lesions with cavities in dentin | Visual criteria | Carisolv/Gel NaClO (0.25%) pH: 11 (n=15 split tooth) | Applied for 30 seconds, manual mechanical removal with a dentin curette, reapplication and removal until no turbidity is observed, cleaning the cavity with a moistened cotton ball, and final rinse. | Conventional low speed: #3 steel round milling cutter. (n=15, split tooth) | Visual and tactile criteria. | Microbiological analysis: Bacterial deposits were observed in histological sections with toluidine blue by SEM (1000 and 5000×). | The presence of bacterial deposits was statistically higher with CMA (40%) than with RS (13.3%) (p<0,05). | Time: from the beginning of the application or rotation until the end of the removal, counted with a stopwatch. | The DC removal time was statistically higher with CMA (5.17 ± 0.63 min) than with RS (2.72 ± 0.47 min) (p<0.001). |
| Hamama et al. (China, 2013) (26) | 24 permanent molars with carious lesions with cavities in dentin | Visual and tactile criteria (blunt dental probe). | Carisolv/gel NaClO (0.25%) pH: 11 (n=8, split tooth) Papacarie/gel Papain 6000 U/mg pH: 6.1-7.9 (n=8, split tooth) | Applied for 30 s, manual mechanical removal with Carisolv #4 instrument, reapplication, and removal until no turbidity is observed, cleaning with distilled water. | Conventional low speed: #14 round steel cutter (n=8, split tooth) | Detection dye | Histological analysis: Gold-coated buccolingual slices were observed according to the patterns of presence or absence of SL in DT by SEM (1000 and 2000×). Mineral content: Average percentages of triplicate weight measurement of calcium (Ca), phosphorus (P), and Ca/P by SEM-EDX. Microhardness: Vickers HM of RS with single indentation analyzed at five points of distance from the cavity soil (25, 50, 75, 75, 100, and 150 μm) by microhardness tester (50 g/15 s). | Histological analysis: RS showed DT covered by SL. Carisolv showed DT fully or partially covered by SL. Papacarie showed DT with almost total absence of SL Mineral content: The content of Ca, P and Ca/P was similar in the groups (Ca: 29.63 to 32.51 ± 1.9 to 3.35; P: 15.09 to 16.07 ± 0.78 to 1.25; Ca/P: 1.95 to 2.02 ± 0.08 to 0.2) (p ≥0.05). Microhardness: MH was statistically higher with RS (81.96 to 83.88 ± 2.3 to 4.23) than with both CMA at all distances (13.88 to 31.83 ± 1.6 to 4.59) (p<0.001). There was no difference between Carisolv and Papacarie (p≥0.05). | Time: from the beginning of the application or rotation until the end of the removal, counted with a stopwatch. | DC removal time was statistically higher with CMA Carisolv (6.46 ± 1.57 min) than with Papacarie (5.19 ± 0.75 min) and RS (4.14 ± 0.32 min) (p<0.001). There was no difference between Papacarie and RS (p≥0.05). |
| Katirci et al. (Türkiye, 2016) (27) | 40 permanent molars with carious lesions with cavities in dentin | Visual and radiographic criteria with severity 4 out of 5. | Carisolv/Gel NaClO (0.25%) pH: 11 (n=40, split tooth) | Applied for 30 s, manual mechanical removal with Carisolv #2-4 instrument, reapplication and removal until no turbidity is observed, cleaning the cavity with a moistened cotton ball, and final rinse. | Conventional low speed: tungsten carbide burr #016. (n=40, split tooth) | Visual, tactile (dental probe), and detection dye criteria. | Histological analysis: Buccolingual slices observed according to the color pattern by SM (100×; 0.4 µm). Mineral content (n=5 /group): Average percentages of triplicate measurement of Ca, P, and Ca/P weight by SEM-EDX Microhardness: knoop MH was analyzed with quintuplicate indentation at a 25 μm distance from the cavity floor by a microhardness tester (50 g/15 s). | Histological analysis: The presence of RC was statistically higher with CMA (20%) than with RS (5%) (p<0.05). Mineral content: Ca, P, and Ca/P content was similar between both groups (Ca: 44.68 and 37.03 ± 13.4 and 11.72; P: 55.76 and 62.95 ± 13.18 and 11.68; Ca/P: 0.91 and 0.86 ± 0.5 and 0.91) (p≥0.05). Microhardness: MH was statistically higher with RS (40.51 ± 5.78) than with CMA (33.5 ± 6.39) (p<0.05). | NA | NA |
| Nair et al. (India, 2018) (28) | 80 permanent molars with a carious lesion in the cavity in the dentin | Visual criteria | Carisolv/Gel NaClO (0.25%) pH: 11 (n=20, split tooth) Papacarie/gel Papain 6000 U/mg pH: 6.1-7.9 (n=20, split tooth) Carie Care/gel Papain pH: 6-7 (n=20, split tooth) | Applied for 30 s, manual mechanical removal with dentin curette, reapplication, and removal until no turbidity is observed, rinse with distilled water. | Conventional high speed: tungsten carbide burr. (n=20, split tooth) | Visual and tactile criteria. | Mineral content (n=5/group): Ca/P weight average percentages by SEM-EDX. Bond strength (n=15/group): Bonding of RD (11 mm thick) to resin until recording fracture observed with microtraction in MPa by UTM (5mm/min). | Mineral content: Ca/P content was similar between groups (2.08 to 2.17 ± 0.06 to 0.17) (p≥0.05). Bond strength: Bond strength was similar between groups (20.3 to 22 ± 2.24 to 3.85 MPa) (p≥0.05). | NA | NA |
| Santos et al. (Brazil, 2020) (2) | 60 permanent molars with a carious lesion in the cavity in the dentin | Visual and radiographic criteria with 2/3 of dentin. | Papacarie/gel Papain 6000 U/mg pH: 6.1-7.9 (n=20, split tooth) Brix 3000/gel Papain 3000 U/mg pH: 7 (n=20, split tooth) | Applied for 40 s (Papacarie) and 120 s (Brix 3000), manual mechanical removal with a dentin curette, reapplication, and removal until no turbidity is observed, cleaning the cavity with a moistened cotton ball. | Conventional low speed: #5 carbide round end mill. (n=20, split tooth) | Visual and tactile criteria (dental probe). | Microhardness: knoop MH was analyzed with quadrupled indentation at 0, 50, 100, and 150 μm distance from the cavity floor using a microhardness tester (25 g/5 s). | Microhardness: The change in MH was similar in the groups at all measurement points (43.23 to 48.54 ± 13.26 to 22.40) (p≥0.05). | Time: from the beginning of the application or rotation until the end of the removal, counted with a stopwatch. | DC removal time was statistically superior among all groups, being higher in Papacarie (Median 1,84 min), followed by Brix 3000 (Median 1.42 min) and RS (0.9 min) (p<0.05). |
| Thomas et al. (India, 2020) (29) | 40 permanent molars with carious lesions with cavities in dentin | Visual, tactile, and tomographic criteria. | Carisolv/gel NaClO (0.25%) pH: 11 (n=40, split tooth) Carie Care/gel Papain pH: 6-7 (n=40, split tooth) | Applied for 60 s (Papacarie) and 30 s (Carie Care), manual mechanical removal with dentin curette, reapplication, and removal until no turbidity is observed, cleaning with water. | Conventional low speed: round milling cutter #0.012 and 0.014. (n=40, split tooth) | Visual, tactile (dental probe), and dye detection criteria. | Radiographic: Differential ECV observed between pre- and post-experiment by CBCT. | The change in ECV was statistically lower with Carisolv and Carie Care (≈25 to 30%) than with RS (≈110%) (p<0.05). There was no difference between Carisolv and Carie Care (p≥0,05). | Time: from the beginning of the application or rotation until the end of the removal, counted with a stopwatch. | DC removal time was statistically higher in Carisolv (3.25 ± 0.7 min), followed by Carie Care (3.08 ± 0.87 min) than with RS (1.92 ± 0.42 min) (p<0.05). There was no difference between Carisolv and Carie Care (p≥0.05). |
Discussion
Effective removal of carious tissue is a crucial factor for preserving dental integrity and preventing dental complications. The present systematic review demonstrated that the removal of DC was effective with CMAs but was more efficient with RS. In addition, CMAs proved to be less invasive towards the treated dentin; however, these agents affected the MH of the adjacent surfaces to a greater extent.
Quality of studies included
This review incorporated in vitro studies on DC removal which can be analyzed by histological, microbiological, chemical, radiographic, and physical-mechanical methods due to their noninvasive nature. Low risk of bias was present in most of the studies (2, 22, 23, 26, 27, 29), especially those with histological and microbiological measurements (22, 23, 26, 27), while the studies with a lack of pre-experiment measurement or unclear statistical analysis presented a moderate risk of bias (24, 25, 28).
Primary outcomes
The studies based on quantitative histological analysis of DC removal were consistent in obtaining significantly better results with RS compared to Carisolv according to results of the quantity or presence of RC and ECV (22, 24, 27). Likewise, although only one investigation qualitatively analyzed DC with SEM, and described optimal results with Papacarie, partially optimal results with Carisolv and non-optimal results with RS when evaluating whether DT were covered with SL (26). In the first studies on Carisolv, it was found that DT were partially optimal (30).
The microbiological results of the DC removal techniques were homogeneous in the two selected studies. In both cases, the presence of microbial deposits in the DEJ was examined after DC removal with Carisolv and RS (23, 25). In both studies, a significantly greater presence of microbial deposits was observed with Carisolv than with RS (23, 25). One study reported efficacy with Carisolv for macroscopic removal of DC but described the presence of RC mainly in the DEJ (30).
Further studies are needed to verify whether antimicrobial agents help to adequately seal the DT after selective removal, and thereby allow blocking the access of cariogenic nutrients to the residual bacterial colonies and subsequently inactivating the progress of the DC lesion (31).
The studies evaluating chemical content included elements commonly found in dentin tissues, such as Ca, P, and Ca/P, which in case of loss would be compatible with demineralization (32). EDX microanalysis was complementary to the morphological analysis by SEM in the studies analyzed. The results showed no differences in the calcium and phosphorus with the use of RS, Carisolv, Papacarie, or Carie Care (26-28).
Only one study included radiographic analysis comparing the efficacy of the techniques with high accuracy using CBCT and reported a significantly greater change in ECV with RS compared to Carisolv and Carie Care (29). This could be compatible with the invasion of non-infected carious dentin. The use of radiographs is common in the in vivo diagnosis of DC and therefore has clinical relevance (33). A technique is not only valued for eliminating DC but also for being minimally invasive (34). Currently, the idea of preserving dentin affec- ted by internal caries and healthy dentin is accepted, but not dentin that is infected with external caries (35).
Two studies on physical properties such as MH reported significant positive differences with RS versus Carisolv and Papacarie (26, 27), while another study described similarity between the types of CMA (36). Another study reported similar results between RS, Papacarie, and Brix 3000 (2) suggesting that CMA leaves residual dentin with lower hardness compared to RS. Nonethe- less, more studies are needed to achieve a more accurate conclusion.
Bond strength is a mechanical property used to assess dentin adhesion. The only study that compared this variable found no differences among RS, Carisolv, Papacarie, and Carie Care in relation to RD bonded to resin (28). With this limited evidence, further research is needed as the type of dentin removed may affect the bond strength of the future restoration. Dentin affected with internal caries becomes a substrate with a lower success rate than healthy dentin due to the collapse of the collagen network or loss of hydro- xyapatite that affects the penetration and polymerization of resin monomers (35, 37).
Secondary outcomes
Efficiency for removal resulted from shorter to longer time in RS with low speed was found in Brix 3000, Papacarie, Carie Care, and Carisolv (2, 22-26, 29). Regarding the results of CMA, one study reported a shorter removal time with Papacarie vs. Carisolv (26), while another study described a similar removal time on comparing Carisolv and Carie Care (29). The introduction of a caries-detecting dye in some studies (24, 26) could explain the variability in the time result, suggesting the need to consider this factor in the analysis.
From the comparisons among the different CMAs, the trend in the results showed that Carisolv required a longer removal time versus other CMAs, unlike Brix 3000, which showed higher performance, possibly because its bioencapsulation type presentation intensifies the enzymatic action, achieving more rapid removal (2).
Clinical implications
Dentists need to support their clinical decisions based on solid evidence. These findings offer valuable insights for improving practices in the treatment of DC in permanent teeth using RS and CMA methods. The possibility of selective removal of carious dentin without pain or prior application of local anesthesia is a major advantage of CMA over RS. In addition, the use of RS requires greater care to avoid invasive removal of healthy tissue, which is a factor of failure in the restoration of both primary and secondary caries (34,38). Likewise, both in in vitro studies and in clinical trials, it has been reported that although CMA demonstrate the ability to remove DC, they require more time compared to RS, and this may affect patient comfort.
Limitations
The studies included in this review were of high-moderate quality, and therefore, the interpretation of the results should be made with caution as the studies involved in vitro experiments that do not constitute a real clinical situation. In addition, the differences in the time and DC removal criteria and types of CMA in the studies included, did not allow a meta-analysis to be performed.
Carisolv was the CMA most frequently evaluated, suggesting the need to explore more agents such as Papacarie, Brix 3000, and Carie Care with standardized results.
Conclusions
In conclusion, this systematic review showed that CMAs were a good option for the removal of caries with less invasion to dentin tissues than RS. However, the use of CMAs decreased the hardness of the surfaces and required a longer removal time. The results are not definitive due to the limited quality and design of the in vitro studies evaluated.
List of abbreviations
Ca (calcium)
CBCT (cone beam computed tomography)
ECV (extracted caries volume)
CM (confocal microscopy)
CMA (chemical-mechanical agents)
DC (dental caries)
DEJ (dentin-enamel junction)
DT (dentin tubules)
EDX (energy dispersive X-ray system)
MH (microhardness)
JBI (Joanna Briggs Institute)
MPa (megapascal)
NaClO (sodium hypochlorite)
OM (optical microscopy)
P (phosphorus)
RC (residual caries)
RD (residual dentin)
RS (rotary systems)
SE (standard error of the mean)
SEM (scanning electron microscopy)
SL (smear layer)
SM (stereoscopic microscopy)
UTM (universal testing machine)
Author contributions statement
Conceptualization and design: J.M.Q.R and S.M.C.
Literature review: J.M.Q.R. and S.M.C.
Methodology and validation: J.M.Q.R. and C.M.S.
Formal analysis: J.M.Q.R. and C.M.S.
Investigation and data collection: J.M.Q.R., K.M.C.S and J.A.D.V.
Data analysis and interpretation: J.M.Q.R., K.M.C.S and J.A.D.V.
Writing-original draft preparation: J.M.Q.R., S.M.C. and C.M.S.
Writing-review & editing: J.M.Q.R., K.M.C.S. and J.A.D.V.

